


Endometriosis vs polycystic ovaries can look confusing. Learn the warning signs, key PCOS differences, fertility effects, diagnosis, treatment, and whether both can occur.
Introduction
When you compare endometriosis vs polycystic ovaries, it is easy to assume they are similar because both involve the ovaries, periods, and fertility. They are actually different conditions with different causes, symptoms, diagnostic pathways, and treatments.
That distinction becomes especially important when an ultrasound shows multiple follicles and you are also experiencing severe menstrual pain. Does that mean you have PCOS? Could the pain be endometriosis? Or could you have both?
In this guide, we will break down PCOS vs endometriosis, explain what “polycystic ovaries” really means, discuss whether you can have both conditions, and look at diagnosis, fertility, and treatment.
Endometriosis vs Polycystic Ovaries: What Is the Difference?
Endometriosis and polycystic ovaries involve different biological processes, symptoms, and diagnostic pathways, so distinguishing them is essential for appropriate treatment and fertility planning.
What is endometriosis?
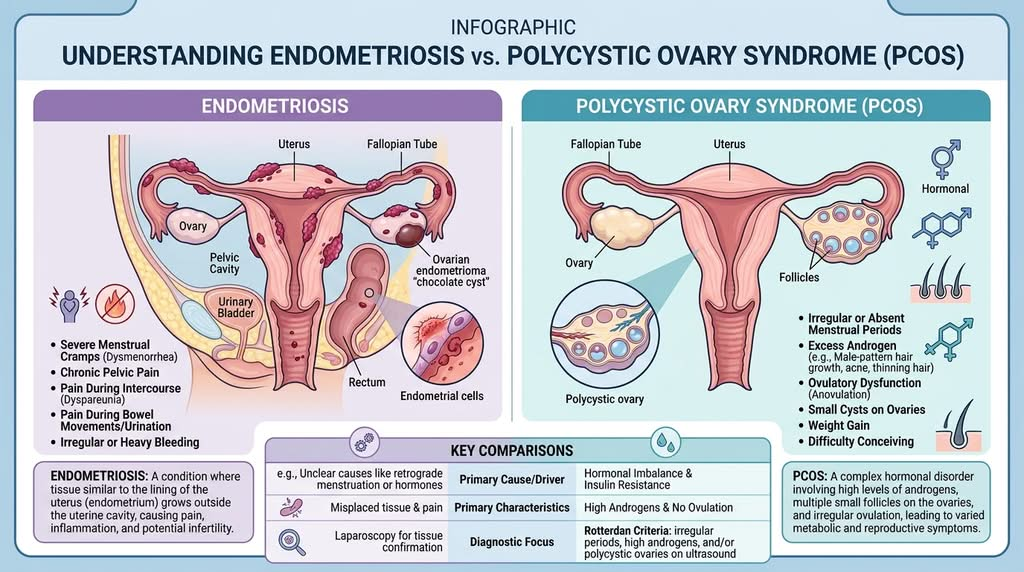
Endometriosis is a chronic inflammatory gynecological disease in which tissue resembling endometrial tissue is found outside the uterus. It may involve the ovaries, pelvic peritoneum, bowel (bowel endometriosis), bladder, or other pelvic structures and can lead to inflammation, adhesions, endometriomas, and pain.
Common endometriosis symptoms include:
- Painful periods,
- Chronic pelvic pain,
- Pain during sex,
- Bowel or bladder pain
- Difficulty conceiving.
ACOG describes endometriosis as a chronic inflammatory disorder involving endometriosis lesions outside the uterus, and its 2026 diagnostic guidance emphasizes clinical, imaging, and surgical evaluation.
What are polycystic ovaries?
“Polycystic ovaries” usually describes an ovarian appearance in which many small follicles are seen on ultrasound. These are follicles, not simply large ovarian cysts. Some people have this ovarian morphology without having polycystic ovary syndrome.
The 2023 international PCOS guideline notes that ultrasound definitions of polycystic ovarian morphology have evolved with improved technology and that interpretation depends on factors including equipment, technique, age, and operator expertise.
Are polycystic ovaries the same as PCOS?
No. Polycystic ovaries and polycystic ovary syndrome are not interchangeable terms.
PCOS is a broader endocrine and reproductive syndrome. It can involve irregular ovulation, elevated androgen activity, acne, increased facial or body hair, and metabolic abnormalities.
A person can have polycystic ovarian morphology without having the full syndrome. Likewise, PCOS does not depend exclusively on seeing a particular ovarian appearance on an ultrasound.
So, when looking at endometriosis vs polycystic ovaries, do not treat an ultrasound finding as the final diagnosis. It is one piece of a much larger clinical puzzle.

PCOS vs Endometriosis: Key Differences at a Glance
The simplest way to understand PCOS vs endometriosis is to compare their biological drivers, typical symptoms, reproductive effects, and treatment strategies side by side.
| Feature | PCOS | Endometriosis |
| Main condition | Endocrine and reproductive disorder | Chronic inflammatory gynecological disease |
| Main biological issue | Ovulatory dysfunction and/or androgen excess | Endometrial-like lesions outside the uterus |
| Irregular periods | Common | May occur but is not defining |
| Severe period pain | Not a classic defining symptom | Common |
| Chronic pelvic pain | Can occur | Common |
| Pain during sex | Possible | Common |
| Acne | Common with androgen excess | Not a defining feature |
| Excess facial/body hair | Can occur | Not typical |
| Polycystic ovarian morphology | May be present | Not the defining feature |
| Ovarian endometrioma | No | Can occur |
| Fertility problems | Often related to irregular ovulation | Can involve inflammation, adhesions, ovarian or pelvic disease |
| Typical diagnostic approach | Clinical history, examination, laboratory evaluation and/or ultrasound | Clinical assessment, imaging and selected surgical evaluation |
| Main treatment approach | Hormonal, metabolic, reproductive and lifestyle management | Pain control, selected surgery and hormonal therapy for endometriosis |
The comparison is useful, but remember that medicine rarely fits into perfectly separated boxes. Some symptoms overlap, and that is precisely why a proper evaluation matters.
PCOS vs Endometriosis Symptoms
Symptoms can point toward one condition or the other, but overlap is common, so symptom patterns should guide evaluation rather than replace diagnosis.
Symptoms more commonly associated with PCOS
PCOS frequently affects ovulation and androgen activity. Common signs can include:
- Irregular or infrequent periods
- Missed periods
- Difficulty predicting ovulation
- Acne
- Increased facial or body hair
- Scalp hair thinning
- Difficulty becoming pregnant because ovulation is irregular
- Weight or metabolic concerns in some patients
Not everyone with PCOS has all of these symptoms.
Some people have relatively regular cycles but have biochemical or clinical signs of androgen excess. Others primarily experience reproductive difficulties.
Symptoms more commonly associated with endometriosis
Endometriosis has a different clinical pattern, especially when pain is prominent.
Common symptoms include:
- Severe menstrual cramps
- Chronic or recurring pelvic pain
- Pain during or after sexual intercourse
- Pain with bowel movements
- Pain with urination in some cases
- Heavy or painful menstrual bleeding
- Abdominal bloating
- Fatigue
- Difficulty conceiving
ACOG describes chronic pelvic pain, particularly around menstruation, as a common symptom and notes that bowel or bladder involvement can produce pain during bowel movements or urination.
The timing of symptoms can be an important clue. Pain that repeatedly intensifies before or during menstruation deserves attention, particularly when it affects normal activities.
Symptoms that can overlap
This is where PCOS and endometriosis become confusing.
Both conditions can be associated with:
- Difficulty becoming pregnant
- Menstrual changes
- Pelvic discomfort
- Ovarian findings on imaging
- Hormonal treatment as part of management
- Significant emotional and quality-of-life consequences
However, the pattern may differ.
Irregular ovulation, acne, excess facial hair, and androgen-related symptoms are more suggestive of PCOS.
Can PCOS Cause Pelvic Pain Like Endometriosis?
PCOS can cause pelvic discomfort in some circumstances, but severe cyclical pelvic pain is not considered its hallmark symptom. If someone diagnosed with PCOS has persistent or disabling period pain, painful sex, bowel pain, or chronic pelvic pain, another condition such as endometriosis may need evaluation.
This distinction matters because it is easy to attribute every pelvic symptom to PCOS after an ultrasound shows multiple follicles. A second diagnosis should be considered when the symptoms do not fit the expected clinical pattern.
Can You Have PCOS and Endometriosis?
Yes. You can have polycystic ovary syndrome and endometriosis at the same time.
Having PCOS does not prevent someone from developing endometriosis, and having endometriosis does not rule out PCOS.
This matters because the two conditions can produce very different problems in the same person.
For example, someone could have PCOS-related irregular ovulation and, separately, endometriosis-related pelvic pain. Treating the hormonal or ovulatory problem may improve one part of the picture without eliminating the pain.
Why both conditions can be missed?
When someone already has a diagnosis of PCOS, irregular periods or fertility problems may be readily explained by that condition, while severe pelvic pain is overlooked. The reverse can also happen.
Diagnostic delays can be particularly frustrating in endometriosis. ACOG’s updated 2026 guidance emphasizes clinical assessment and imaging as ways to support earlier diagnosis rather than relying exclusively on surgical confirmation.
What symptoms may suggest both conditions?
You may need evaluation for both when symptoms include a combination such as:
- Irregular or absent periods
- Difficulty ovulating
- Acne or androgen-related symptoms
- Significant menstrual or pelvic pain
- Pain during sex
- Bowel or bladder symptoms around menstruation
- Difficulty conceiving
- Polycystic ovarian morphology alongside severe pelvic pain
Having these symptoms does not prove that you have both conditions. It simply means that a broader assessment may be appropriate.
How Are PCOS and Endometriosis Diagnosed?
Although both conditions can involve the ovaries and reproductive system, their diagnoses rely on different clinical criteria and investigative pathways.
How PCOS is diagnosed?
PCOS diagnosis is based on the overall clinical picture.
Depending on the individual, a healthcare professional may assess:
- Menstrual and ovulation patterns
- Signs of androgen excess
- Hormonal blood tests
- Physical examination
- Metabolic health
- Pelvic ultrasound when appropriate
The traditional Rotterdam framework considers combinations of oligo-anovulation, hyperandrogenism, and polycystic ovaries, after other causes have been excluded.
This is why a report that says “polycystic ovaries” should not automatically be translated into “you have PCOS.”
How polycystic ovaries appear on ultrasound?
Polycystic ovarian morphology typically means many small follicles or increased ovarian volume on ultrasound. These follicles are not the same as the large pathological ovarian cysts many patients imagine. Modern ultrasound technology has changed the way ovarian morphology is assessed, which is one reason reports should be interpreted in the context of age, symptoms, clinical findings, and the method used.
How endometriosis is diagnosed
Endometriosis diagnosis begins with the clinical picture, including pain pattern, menstrual history, reproductive goals, and examination. Imaging can identify many forms of ovarian and deep disease, but no single test excludes all endometriosis. In 2026, ACOG released dedicated diagnostic guidance covering clinical, imaging, and surgical evaluation of suspected endometriosis.
Ultrasound
A targeted transvaginal ultrasound can help identify ovarian endometriomas and some forms of deep endometriosis, particularly when performed by an experienced practitioner. ESHRE recommends ultrasound or MRI during the diagnostic work-up but emphasizes that negative imaging does not completely exclude endometriosis, especially superficial disease.
MRI
MRI can provide detailed information about the location and extent of suspected deep endometriosis and may be useful for treatment planning. It is particularly valuable when doctors need to understand how disease relates to structures such as the bowel, bladder, ureters, or other pelvic organs. However, MRI is not a universal “yes or no” test for all endometriosis.
Laparoscopy
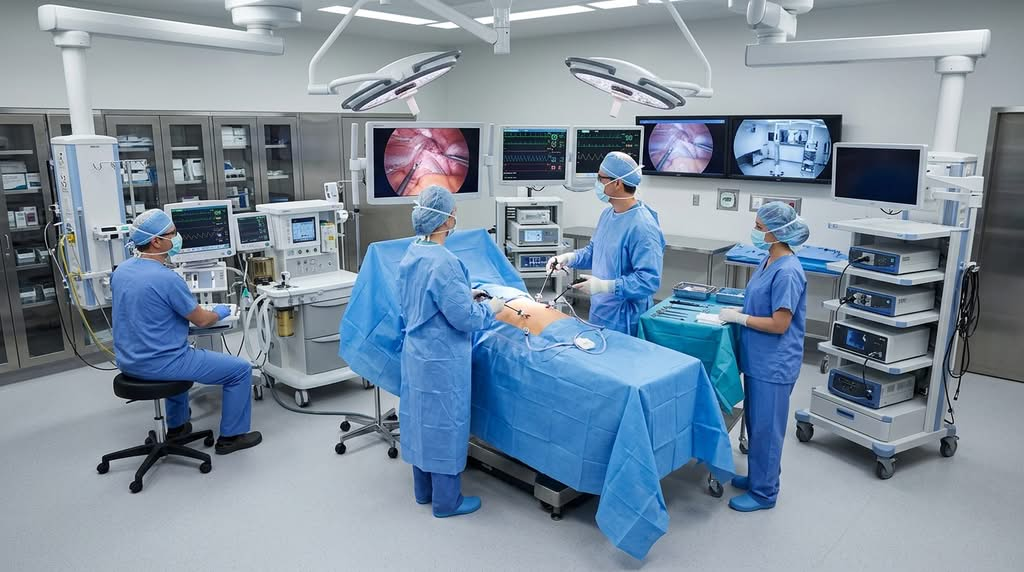
Laparoscopy allows a surgeon to directly inspect the pelvis and, when appropriate, treat visible endometriosis during the same procedure. ESHRE recommends considering laparoscopy in selected patients when imaging is negative and empirical treatment has been unsuccessful or inappropriate.
PCOS and Endometriosis: How Can They Affect Fertility?
Both conditions can affect fertility, but they usually do so through different mechanisms; understanding those mechanisms helps determine what kind of fertility assessment may be useful.
How PCOS affects ovulation?
PCOS commonly interferes with regular ovulation. When ovulation occurs infrequently or unpredictably, conception can become more difficult because there are fewer regular opportunities for an egg to be released. Fertility treatment may therefore focus on restoring or inducing ovulation when pregnancy is desired, depending on the individual’s circumstances.
How endometriosis can affect fertility?
Endometriosis may affect fertility through inflammation, adhesions, endometriomas, and changes in pelvic anatomy. Severe disease can distort the relationship between the ovaries, fallopian tubes, and surrounding tissues. ACOG notes that endometriosis can interfere with fertility and, in severe disease, adhesions may affect the fallopian tubes.
Having both conditions and fertility
When someone has both PCOS and endometriosis, fertility planning may need to address ovulation and pelvic disease separately. Age, ovarian reserve, tubal factors, disease extent, previous surgery, and pregnancy goals all matter. Dr. Lucas Minig’s endometriosis treatment planning includes fertility-sparing strategies when clinically appropriate, rather than treating surgery as an isolated procedure.
How Are PCOS and Endometriosis Treated?
Treatment is highly individualized: PCOS management generally addresses hormonal, metabolic, and reproductive issues, while endometriosis treatment targets pain and disease-related symptoms.
PCOS treatment
PCOS treatment depends heavily on your priorities.
If pregnancy is not currently desired, management may focus on menstrual regulation and androgen-related symptoms. If pregnancy is a goal, improving ovulation may become the central objective.
Depending on the patient, treatment can include:
- Lifestyle and metabolic interventions
- Hormonal contraception
- Medications for androgen-related symptoms
- Metabolic medications where appropriate
- Ovulation-inducing treatment
- Fertility treatment
The important point is that there is no universal PCOS treatment plan.
Your symptoms, reproductive goals, metabolic health, and personal preferences should guide management.
Endometriosis treatment
Endometriosis can be managed using pain-relieving medication, hormonal therapies, surgery, or combinations of these approaches.
ACOG lists NSAIDs and hormonal treatments among medications used for endometriosis and notes that treatment choices depend on symptoms, disease extent, and reproductive plans.
Common medical approaches can include:
- NSAIDs and other pain relievers
- Combined hormonal contraceptives
- Progestin-based therapies
- GnRH agonists or antagonists
- Other hormonal strategies in selected patients
The choice should be individualized because every treatment has potential benefits, limitations, and side effects.
Dr. Lucas Minig’s treatment approaches pain medication for endometriosis and hormonal therapy as part of endometriosis management before or alongside selected surgical treatment.
When surgery may be considered for endometriosis?
Surgery may become an option when symptoms remain significant despite medical management, when certain forms of disease are present, or when fertility and pelvic anatomy need particular consideration.
Potential procedures may include:
- Excision of deep endometriosis
- Removal of ovarian endometriomas
- Adhesiolysis
- Selected bowel procedures
- Selected bladder or ureteral procedures
Dr. Lucas Minig’s practice in Valencia describes laparoscopic management of deep and severe pelvic endometriosis, including ovarian endometrioma cystectomy, excision of deep lesions, pelvic adhesion removal, and selected bowel or bladder procedures.

When Should You See an Endometriosis Specialist?
Specialist assessment may be appropriate when pelvic pain is severe, persistent, unexplained, or associated with fertility problems, bowel symptoms, bladder symptoms, endometriomas, or suspected deep disease.
You may want to discuss specialist evaluation if you experience:
- Severe period pain that disrupts daily activities
- Persistent pelvic pain
- Pain during sexual intercourse
- Pain with bowel movements during menstruation
- Urinary pain that appears cycle-related
- An ovarian endometrioma
- Suspected deep endometriosis
- Persistent symptoms despite hormonal treatment
- Unexplained fertility difficulties
- Repeatedly abnormal pelvic imaging
You also do not need to wait until the pain becomes unbearable.
Dr. Lucas Minig specializes in minimally invasive gynecologic surgery and describes care for deep and severe pelvic endometriosis in Valencia. His practice also offers video consultations for international patients, which can be useful when someone is seeking a specialist opinion before traveling to Spain.
Conclusion
The key difference in endometriosis vs polycystic ovaries is that they represent different medical problems. PCOS is a broader hormonal and reproductive syndrome, while endometriosis involves endometriosis lesions outside the uterus and can cause inflammation, adhesions, pelvic pain, endometriomas, and fertility difficulties. Just as importantly, polycystic ovaries are not automatically the same thing as PCOS. And yes, you can have PCOS and endometriosis together. When symptoms do not fit neatly into one diagnosis, a detailed evaluation can help determine whether you need hormonal management, endometriosis treatment, fertility support, or specialist surgical assessment from Dr. Lucas minig.
FAQ’s
Is PCOS worse than endometriosis?
Neither condition is automatically worse. PCOS can affect ovulation, hormones, and metabolic health, while endometriosis may cause significant pelvic pain, adhesions, ovarian disease, and fertility problems. Severity varies considerably between individuals.
Can you have PCOS without ovarian cysts?
Yes. PCOS is not simply a disease of ovarian cysts. Diagnosis relies on the overall clinical picture, which can include ovulatory dysfunction and hyperandrogenism. An ultrasound showing or not showing polycystic ovarian morphology does not independently determine the diagnosis.
Can you have endometriosis with regular periods?
Yes. Regular menstrual cycles do not rule out endometriosis. Some people have regular periods but develop significant pelvic pain, painful intercourse, bowel symptoms, ovarian endometriomas, or fertility difficulties.
Can PCOS cause severe period pain?
Severe period pain is not the hallmark symptom of PCOS. If pain is intense, persistent, or repeatedly linked to menstruation, other causes—including endometriosis, adenomyosis, fibroids, or ovarian conditions—may need to be considered.
Can endometriosis cause irregular periods?
It can be associated with menstrual changes, although irregular ovulation and strongly irregular cycles are more characteristic of PCOS. A person with irregular periods and significant pelvic pain may need assessment for more than one condition.
Can you have both PCOS and endometriosis?
Yes. PCOS and endometriosis can occur in the same person. When they coexist, symptoms such as irregular cycles, infertility, pelvic pain, or ovarian findings can overlap. A detailed assessment is therefore important to identify and manage each condition appropriately.


